

Table of Contents
Most patients come in asking whether dental implants will feel permanent. The honest answer depends entirely on one thing: whether the implant successfully fuses with your jawbone. That fusion is called osseointegration, and it is what separates a dental implant that lasts a lifetime from one that fails within a few years.
It shapes how you prepare for treatment, how you approach recovery, and what questions to ask before moving forward. At our practice in Indianapolis, we walk through it with every implant patient because the patients who understand it tend to have better outcomes.
What Is Osseointegration?
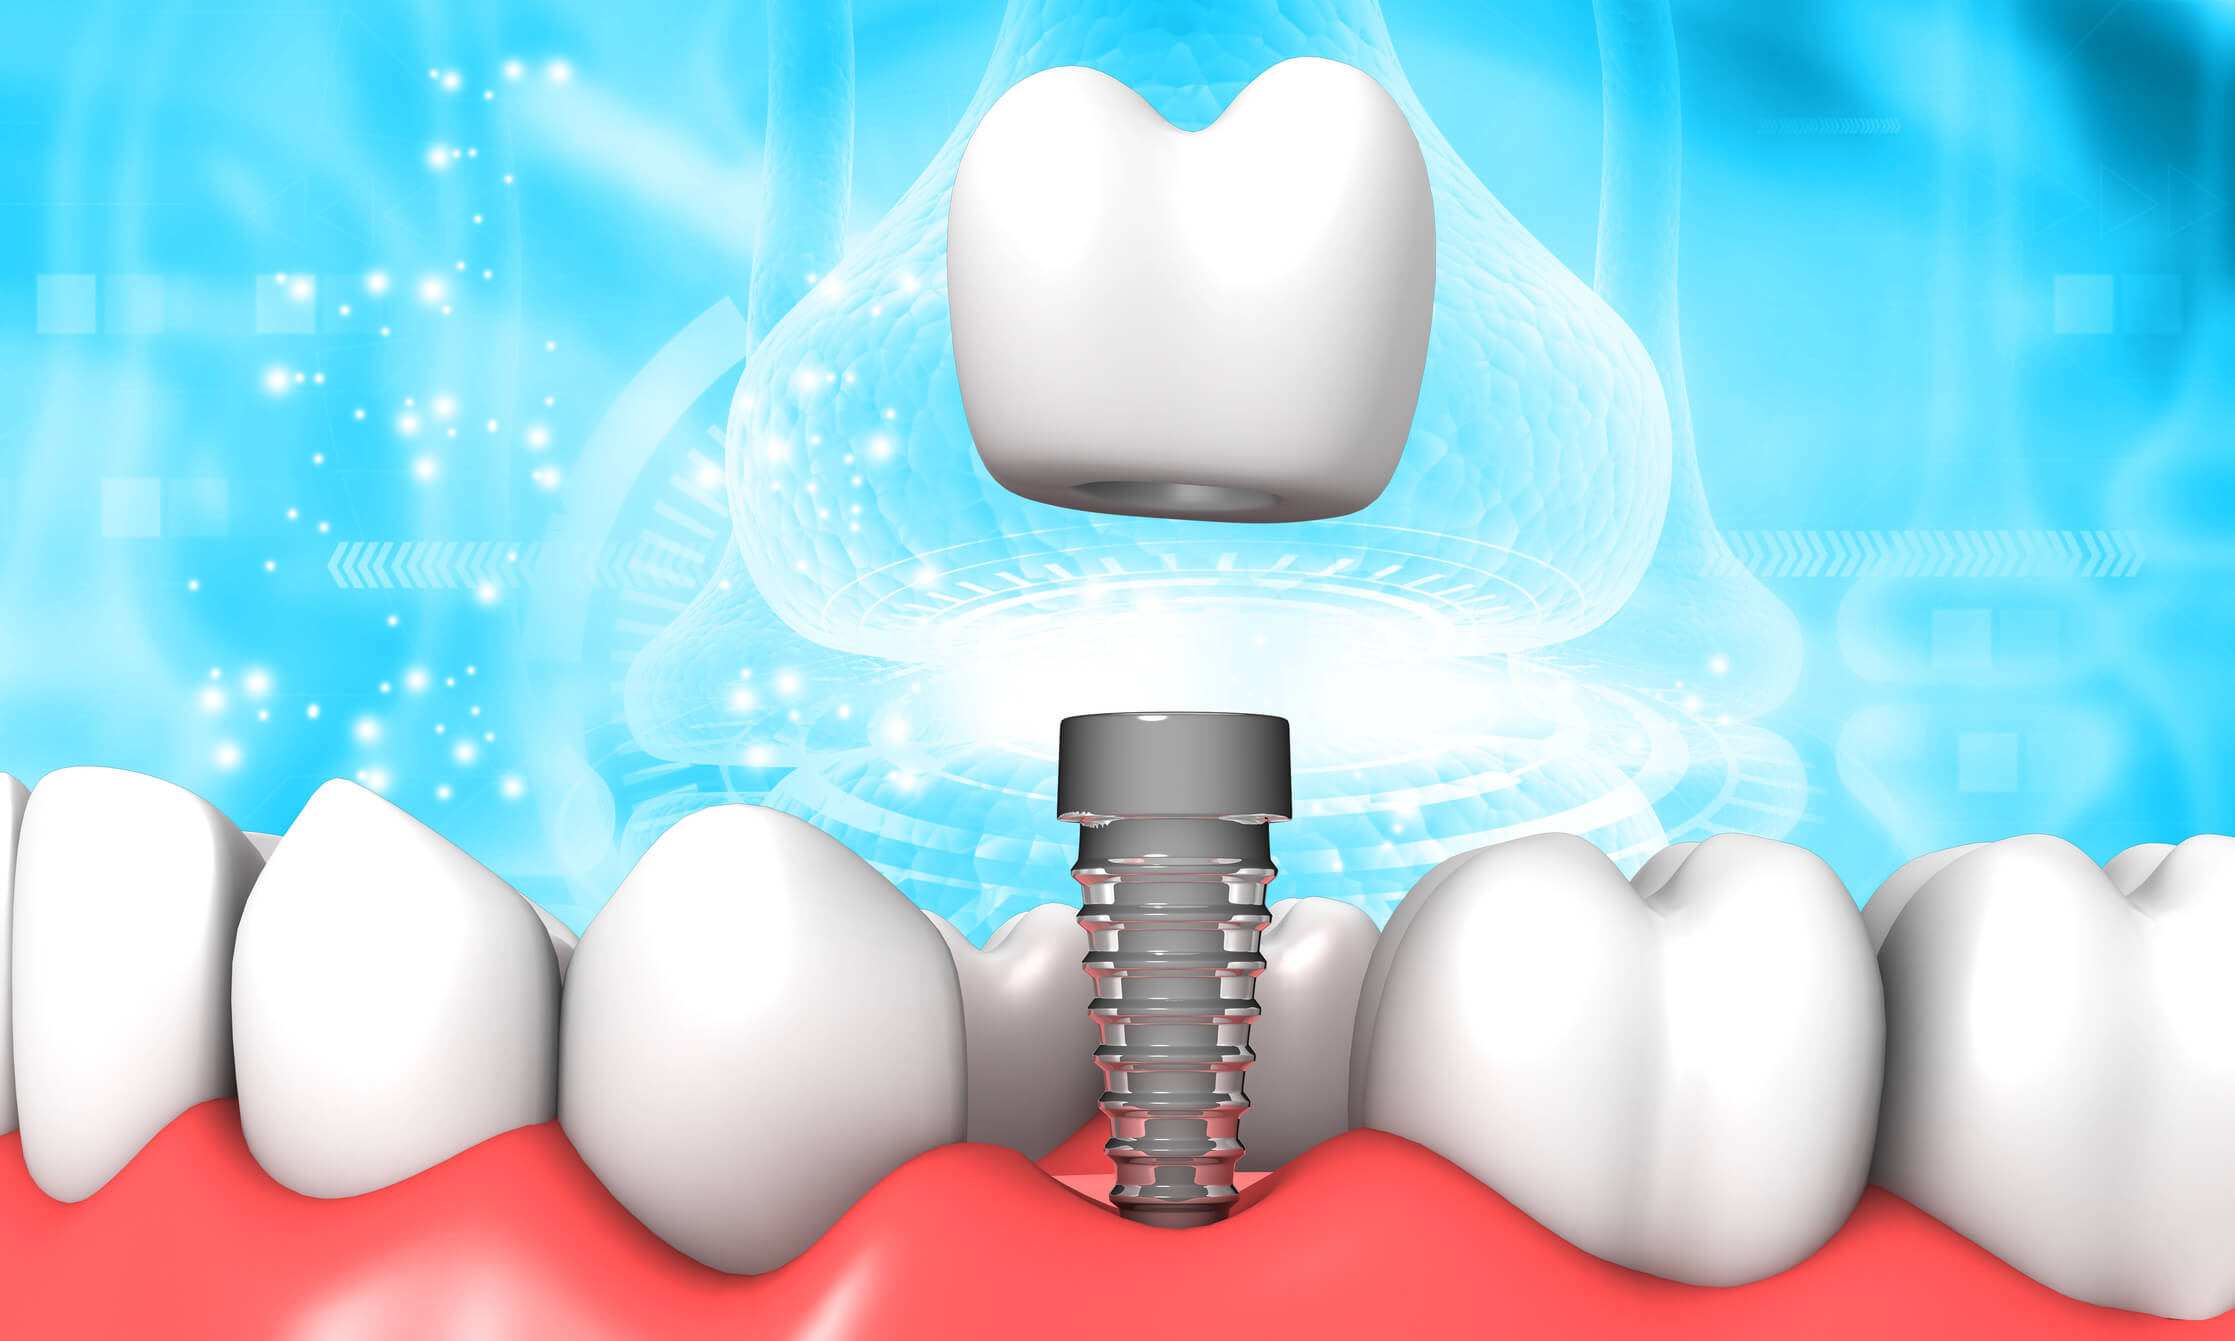
Put simply, osseointegration is the process by which your jawbone grows into and around a dental implant, forming a bond that works like a natural tooth root. The implant post itself is made from titanium, a material the body does not reject. Once placed, it does not just sit in the bone. The surrounding tissue responds to it, bone cells migrate toward the surface, and over weeks and months, new bone forms around the post.
The process was first observed in the 1950s by Swedish researcher Per-Ingvar Brånemark, who discovered almost by accident that titanium could permanently fuse with living bone. His findings became the foundation of modern implant dentistry. Practically, it means your body does most of the work. The implant does not stay in place because of adhesive or mechanical pressure alone. It stays because the bone makes it part of itself.
How Do Dental Implants Fuse to Bone?
- Inflammation and Initial Healing
The first few days after placement look like any other surgical healing response. Blood flow increases, the immune system sends cells to clear debris, and the tissue begins to organize for repair. Expected.
- Bone Cell Recruitment
Once inflammation subsides, osteoblasts (the cells that produce new bone) begin to migrate toward the implant surface. They deposit fresh bone matrix directly onto the textured titanium. Modern implant surfaces are specifically engineered to encourage this, with surface treatments that maximize cell attachment and create strong contact between the post and surrounding bone tissue.
- Remodeling and Maturation
New bone is not immediately dense or well-organized. Over the weeks and months that follow, the body refines what it built. Less structured tissue is replaced by denser, more organized bone through a process called remodeling. This is actually the phase most patients do not realize is still happening. The implant shifts from primary stability (the mechanical grip at placement) to secondary stability driven by genuine bone growth, and secondary stability is the benchmark that tells us when the final restoration can safely go in.
- Blood Supply Development
Running alongside bone formation is vascularization, where new blood vessels develop within the healing tissue. Bone-forming cells need oxygen and nutrients throughout the regeneration period, and blood flow is how they get them. Anything that restricts circulation to the site slows healing.
How Long Does Osseointegration Take?
The implant-healing timeline varies among patients, but most cases fall within a predictable range. Initial osseointegration is generally considered substantially complete between eight and sixteen weeks after placement. Full bone maturation, where the surrounding bone has fully consolidated, and the implant has reached complete secondary stability, takes three to six months in most patients.
People with good bone density and well-managed overall health tend to fall on the shorter end. Those with lower bone density or certain health factors may need more time, and honestly, that comes up more often than people expect. We plan for it from the start. Progress is monitored through imaging and clinical evaluations at each stage, and we schedule the restoration based on how integration is actually going, not on a fixed calendar.
What Affects Implant Healing and Integration Success?
Some of these factors are things patients can directly influence. Others need to be identified and planned around before treatment even begins. Either way, all of them get assessed before we recommend proceeding.
- Bone Quality and Volume
The alveolar bone (the part of the jawbone that once held the tooth root) needs enough density and volume to stabilize the implant while healing is still underway. If tooth loss occurred some time before the implant appointment, the bone may already have started shrinking. CBCT scanning and digital imaging during the planning phase tell us whether what’s there is adequate or whether grafting is needed first.
- Health Conditions That Affect Bone Healing
Conditions such as diabetes or osteoporosis have a well-documented effect on bone healing and remodeling. A patient with poorly managed blood sugar, for example, heals more slowly and is more susceptible to infection, both of which can reduce the success of dental implants. Neither condition automatically disqualifies someone, but they do need to be well-controlled before and during treatment. When relevant, we coordinate directly with the patient’s physician.
Beyond systemic health, two lifestyle factors have a particularly direct effect on the reliability of the implant-healing process.
- Smoking
Smoking restricts blood flow to the gums and surrounding bone, directly undermining the vascular environment on which osseointegration depends. The data on this is consistent: patients who smoke fail implants at a meaningfully higher rate than non-smokers. Stopping before surgery and staying stopped through the healing period substantially reduces this risk.
- Oral Hygiene
Gum disease is one of the more significant threats to long-term implant stability, whether it exists before placement or develops afterward. The bacteria responsible for periodontal disease can also attack the tissue around an implant, leading to peri-implantitis, a condition that can steadily compromise the bone-implant connection if left untreated. Good oral hygiene before and after surgery is not optional.
- Surgical Precision
How the implant is placed has a direct bearing on the onset of osseointegration. The preparation of the bone site, the positioning of the post, and the management of the surrounding tissue all shape the quality of primary stability on surgery day. Pre-surgical planning guided by CBCT imaging ensures the implant makes optimal contact with surrounding bone from the start. Good planning at this stage honestly matters more to long-term stability than most post-operative factors combined.
- Post-Operative Care
The weeks after surgery are when the integration process is most active and most vulnerable. Following post-operative care instructions, keeping follow-up appointments, and avoiding anything that disrupts blood flow or introduces bacterial risk all have a real impact on how well things go.
Why Implants Feel and Function Like Natural Teeth
Patients ask this question more than almost any other. Why does an implant feel like a real tooth when a denture or bridge never quite does?
It comes down to what the implant is anchored to. Because it is fused with the jawbone, chewing forces move directly into the bone, just as they do through a natural root. Dentures distribute pressure across the gum surface. Bridges transfer load to neighboring teeth. Neither one talks to the bone at all, and patients feel that absence.
There is also a longer-term consequence worth knowing. When a tooth is lost and the root is not replaced, the jawbone in that area gradually resorbs over time. An osseointegrated implant continuously stimulates the bone through normal chewing, preserving the volume and structure that support surrounding teeth and the facial contour.
If you are considering implants as a solution for tooth loss, the right starting point is a thorough evaluation of your bone health, medical history, and goals. At Julie L. Stante, DDS, we approach every dental implant consultation with the same care we bring to every other part of our practice. We take the time to answer your questions fully and make sure you have a clear picture before any decisions are made.
We serve patients from Indianapolis, Fishers, Carmel, and throughout Central Indiana. To schedule a consultation, contact our office at 317-579-1875 or request an appointment online.
FAQs
What is osseointegration?
Osseointegration is what happens when the bone in your jaw grows into and around a dental implant over several months. The titanium post does not just sit there held by pressure. Bone cells actually migrate to the surface and build new tissue around it, which is why a well-integrated implant does not depend on adhesive or neighboring teeth to stay put.
How do dental implants stay in place?
Once osseointegration is complete, the implant is held by bone. No adhesive, no suction, no dependence on adjacent teeth. The bond that forms through the healing process is permanent, which is why implants behave so differently from other restorations in everyday use.
How long does osseointegration take?
Most patients reach substantial initial osseointegration somewhere between eight and sixteen weeks after placement, though full bone maturation can take up to six months. A lot depends on bone density, overall health, and how the healing period goes. We do not put the final restoration in on a fixed schedule. We go by what the imaging and evaluations actually show.
What causes poor osseointegration?
Several things can get in the way. Insufficient bone volume, poorly controlled diabetes, active gum disease, smoking, and inadequate post-operative care are the most common. Some of these are things patients can address before treatment starts. Others we need to plan around carefully. Either way, we assess all of them before recommending implant placement.
Does smoking affect how implants heal?
Yes, significantly. Smoking constricts blood vessels in the gums and bone, impairing the healing environment that osseointegration depends on. Patients who smoke have a considerably higher complication rate. Stopping before surgery and staying stopped through healing makes a real difference.
Can patients with diabetes receive dental implants?
Many do, and successfully. But stable blood sugar management is a firm prerequisite. Poorly controlled diabetes slows tissue regeneration, raises infection risk, and can directly interfere with bone healing around the implant. We carefully review health history at the planning stage and work with each patient’s physician when relevant.
What is the difference between primary and secondary implant stability?
Primary stability is the mechanical grip the implant has right after it is placed, based on the physical fit between the post and the prepared bone site. Secondary stability is different. It develops gradually as bone grows into and around the implant surface through osseointegration, and it is what we assess before placing the final restoration. An implant with good secondary stability is one the bone has genuinely accepted.
Do you place dental implants for patients in Fishers and Carmel?
Yes. Dr. Julie Stante serves patients from Indianapolis, Fishers, Carmel, and the broader Central Indiana area. If you are considering implants, we welcome you to schedule a consultation to talk through whether they are the right solution for your situation.